
Planning
Recognizing Opioid Intoxication: Nursing Assessment and Response
Recognizing opioid intoxication early allows nurses to support ventilation, activate emergency resources, administer naloxone when indicated, and monitor for recurrent respiratory depression. Assessment should focus on breathing, oxygenation, level of consciousness, recent opioid exposure, and other
Updated 2026-11-10 · Nursing CE editorial team
Every course included · Instant certificates · Renews yearly, cancel anytime before renewal
- Board-approved provider (CA, FL, NV, NY, PA, OH)
- Contact hours and accepted states listed on every course
- Certificate issued the moment you pass
Quick answer
The most concerning opioid intoxication signs are slowed or ineffective breathing, increasing sedation, reduced responsiveness, and pinpoint pupils, although pupils may not always be constricted. Treat suspected opioid-related respiratory depression as an emergency: support the airway and ventilation, activate the appropriate response, use naloxone according to facility protocol, and continue close monitoring because sedation and respiratory depression can return.
What are the key opioid intoxication signs?
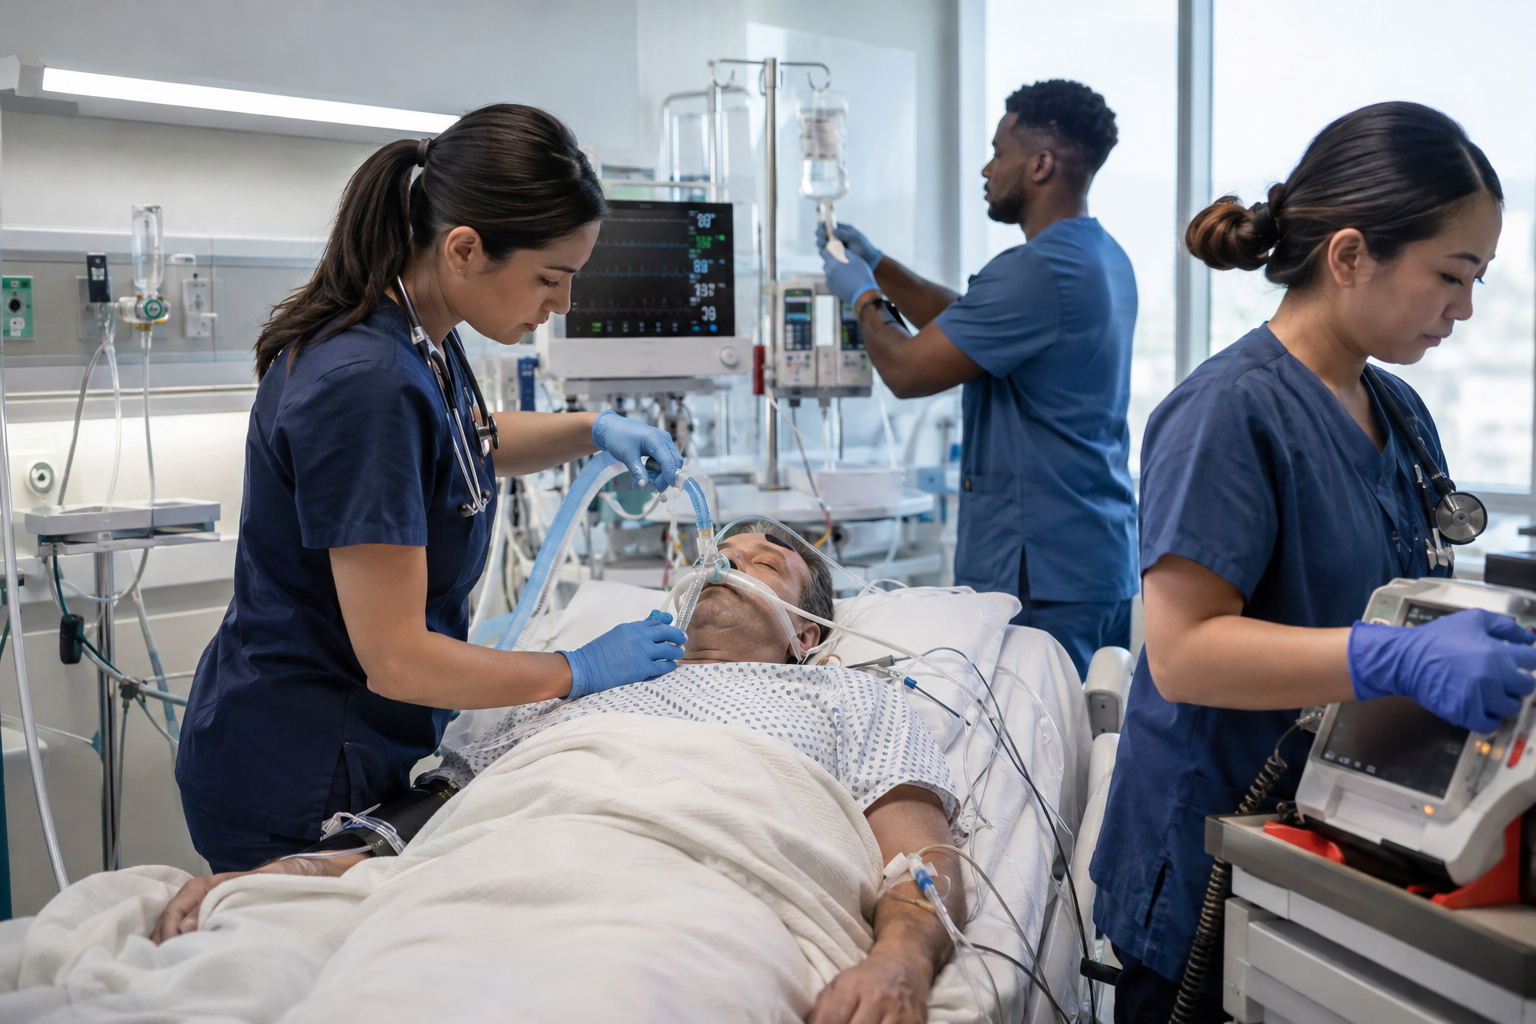
The classic pattern of opioid intoxication includes central nervous system depression, respiratory depression, and constricted pupils. Clinically, respiratory status is the priority. A patient may have slow, shallow, irregular, or absent respirations; reduced chest movement; snoring, gurgling, or other abnormal airway sounds; cyanosis; and declining oxygen saturation.
Changes in consciousness may range from unusual sleepiness to an inability to awaken with verbal or physical stimulation. Other possible findings include decreased bowel sounds, nausea or vomiting, cool skin, low blood pressure, and bradycardia. Findings vary with the opioid, route, amount, co-exposures, tolerance, and underlying health conditions.
Do not rule out opioid intoxication because the pupils are normal or dilated. Hypoxia, co-ingested substances, eye conditions, medications, or certain opioids can alter the expected pupil response. The overall clinical picture—especially ventilation and responsiveness—is more important than any single sign.
How should nurses assess suspected opioid intoxication?
Begin with airway, breathing, circulation, and level of consciousness. Assess respiratory rate, depth, rhythm, chest movement, airway sounds, skin color, oxygen saturation, and the patient’s response to stimulation. A documented respiratory rate alone may miss shallow or ineffective ventilation, so observe the quality of each breath.
Obtain available information about prescribed opioids, recent procedures, medication administration times, transdermal products, infusion devices, substance exposure, and possible co-ingestion of alcohol, sedatives, or other drugs. Review relevant conditions such as sleep apnea, pulmonary disease, renal or hepatic impairment, and prior opioid tolerance.
Use the sedation and respiratory assessment tools required by your organization. Continuous pulse oximetry or capnography may be appropriate when available and ordered or protocol-driven, but monitor data should supplement—not replace—direct bedside assessment. Follow facility escalation criteria and do not leave an unstable patient unattended.
Finish all your CE hours in one place
Unlimited online courses for $29.99 a year, with certificates the moment you pass.
Apple Pay & Google Pay on supported phones Visa · Mastercard · Amex · DiscoverSecure checkout by Stripe
What is the immediate nursing response to respiratory depression?
Suspected opioid-related respiratory depression requires prompt action. Stimulate the patient, position and open the airway, call for emergency assistance or activate the rapid response system, and provide oxygen and ventilatory support as directed by the patient’s condition, your scope of practice, and facility protocol. If the patient has no pulse, begin resuscitation according to current life-support guidance.
Stop or pause opioid administration when permitted by protocol and address removable medication sources, such as a transdermal patch, if directed. Gather relevant medication records, recent vital signs, and information about possible co-exposures for the responding team. Do not delay airway or ventilation support while attempting to confirm the exact opioid involved.
Continue reassessing breathing, circulation, and neurological status throughout the response. If the patient does not improve as expected, consider other or additional causes of altered consciousness and respiratory compromise, including hypoglycemia, stroke, head injury, sepsis, seizures, or intoxication with non-opioid substances.
How does naloxone response guide ongoing care?
Naloxone is an opioid antagonist used to reverse opioid-related respiratory and central nervous system depression. Administer it by the approved route and according to current orders, emergency procedures, and facility protocol. The immediate goal is restoration of adequate ventilation and airway protection, not necessarily complete alertness or elimination of pain.
A response may include improved respiratory rate, depth, oxygenation, or level of consciousness. Naloxone can also precipitate acute withdrawal, particularly in an opioid-dependent patient. Watch for agitation, vomiting, sweating, tachycardia, hypertension, pain, or attempts to leave before evaluation is complete, and protect the patient from aspiration or injury.
A limited or absent response does not remove the need for ventilation and resuscitative care. The opioid exposure may be substantial or prolonged, another substance may be involved, or the condition may have another cause. Continue emergency support, reassessment, and additional treatment as directed by the responding clinician and facility protocol.
Why is monitoring necessary after naloxone?
The effects of some opioids may last longer than the effects of naloxone. Respiratory depression and sedation can therefore recur after initial improvement. Continue frequent assessment of respiratory rate and quality, oxygenation, consciousness, airway protection, circulation, and pain according to the ordered level of care and facility policy.
Escalate promptly if the patient becomes harder to arouse, develops slower or shallower breathing, has decreasing oxygen saturation, or shows other signs of deterioration. Repeat naloxone or advanced airway interventions may be needed under an authorized order or protocol. Patients with long-acting opioid exposure, multiple substances, significant comorbidities, or repeated naloxone needs may require a higher level of monitoring.
Document objective findings, the timeline of changes, interventions, naloxone administration, patient response, notifications, and disposition. Clear handoff communication should include the suspected exposure, last known opioid administration, respiratory trends, response to treatment, and ongoing risks.
Where can nurses complete opioid CE?
Opioid continuing education can reinforce recognition of opioid intoxication signs, safe medication practices, naloxone principles, monitoring, patient education, and documentation. Explore the opioid CE options available on this site and choose courses that match your role and learning needs.
Our All-Access pass costs $29.99 per year and includes every course, self-paced online learning, and instant certificates. It renews yearly, so cancel before renewal if you do not want another year. One free course, Improving Interprofessional Communication and Collaboration, is also available.
Continuing education rules differ by profession, jurisdiction, employer, and renewal cycle. Confirm current opioid education requirements with your nursing board and employer rather than relying on a general hour total. Clinical practice should always follow applicable law, organizational policy, authorized orders, and your scope of practice.